Fluid balance & imbalances
Where body water lives, how the body keeps it level, and what too little or too much looks like.
Body fluids
What body fluids do: carry nutrients to cells and waste away from them; transport hormones, enzymes, platelets, RBCs (red blood cells) and WBCs (white blood cells); help cellular metabolism and digestion; excrete waste; and act as a lubricant.
Fluids and solutes shift between compartments by osmosis, diffusion, active transport and capillary filtration, with help from organs and body systems. Acute and chronic illness, trauma, and some treatments put clients at high risk for fluid, electrolyte and acid-base imbalances, which can be life threatening.
| Compartment | What it is | Share of body water |
|---|---|---|
| ICF (intracellular fluid) | Fluid inside cells; runs cell function and metabolism | About 67% (two-thirds) |
| ECF (extracellular fluid): interstitial | Spaces between cells; includes lymph | 25% |
| ECF: intravascular | Plasma inside the blood vessels | 8% |
| ECF: transcellular | Specialized fluids: cerebrospinal, pleural, peritoneal, pericardial, synovial, digestive juices | A minor amount |
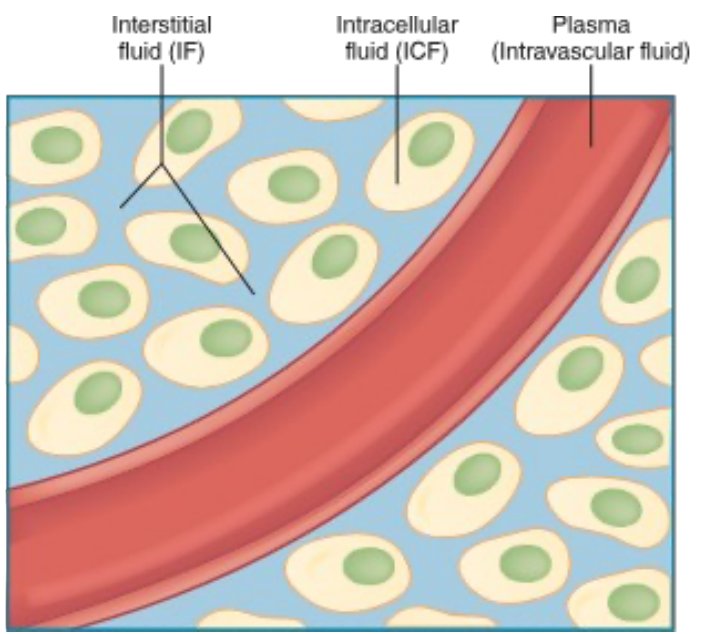
67 · 25 · 8: most water is in the cells, a quarter sits between them, and only a sliver is in the blood.
- Water is 50–60% of an adult's body weight.
- Osmosis: water moves across a membrane from the weaker (more dilute) side to the stronger (more concentrated) side. No energy needed.
- Diffusion: solutes (like electrolytes) spread from high concentration to low. No energy needed.
- Active transport: uses energy (ATP, adenosine triphosphate) to move solutes from low concentration to high, like the sodium–potassium pump.
- Filtration: pressure pushes fluid out of the capillaries into the tissues.
- Sensible losses can be measured (urine, sweat, liquid stool). Insensible losses can't (breathing, evaporation from the skin, water in formed stool).
- Third spacing: fluid gets trapped in a body space where the body can't use it (burns, cirrhosis, pancreatitis). It's still in the body, but blood volume drops.
Intake, output & the kidneys
Intake
- Anything by mouth
- IV (intravenous) fluids
- Feeding tubes
Output
- Urine
- Bowel movements
- Drains
- NG (nasogastric) tube drainage
- Vomiting
- Record I&O (intake and output) per facility or unit protocol. Daily intake and output should balance.
- Fluid intake is regulated mainly by the thirst mechanism in the hypothalamus.
- The renal system (kidneys) is the main regulator of fluid volume. Water is the main solvent; solutes are electrolytes and nonelectrolytes.
| Kidney function test | Normal |
|---|---|
| BUN (blood urea nitrogen) | 10–20 mg/dL |
| Creatinine | Female 0.5–1.2 mg/dL · Male 0.6–1.3 mg/dL |
Measure all I&O in mL: 1 oz = 30 mL (an 8-oz cup is 240 mL). Intake includes foods that melt at room temperature, IV flushes and IV medications, tube feedings and irrigants. Output includes blood, emesis, diarrhea, and wound or tube drainage. Report urine output under 30 mL/hr.
Measure with calibrated containers, read at eye level. Total I&O at least every 8 hours: intake minus output; a negative number means a deficit. For incontinence briefs, weigh them: 1 g = 1 mL. Weigh the client daily at the same time, after voiding, in the same type of clothes (same linens on a bed scale).
Serum osmolality: how the body stays level
Serum osmolality measures the concentration of solutes to water in the blood. It's the body's gauge of fluid balance.
Normal serum osmolality: 285–295 mOsm/kg. Osmolality is just a "fancy way to look at concentration."
Blood too concentrated (osmolality ↑)
- Thirst kicks in
- ADH (antidiuretic hormone) is released, so the kidneys hold on to water and make less urine
Blood too dilute (osmolality ↓)
- Thirst shuts off
- Less ADH, so the kidneys let more water go
Fluid imbalances
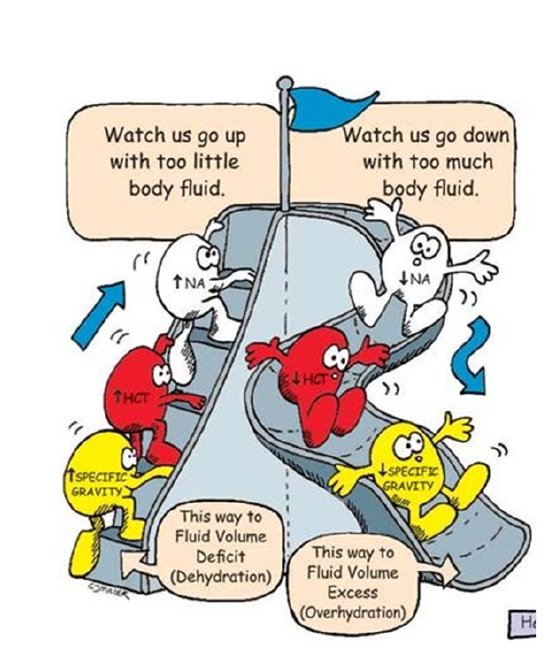
Dehydration = a loss of water (or lack of water intake) without a loss of sodium. Sodium stays, so blood sodium rises (hypernatremia) and serum osmolality rises. Water moves out of the cells into the vascular space. Essentially a total loss of body water.
| Dehydration | Hypovolemia (fluid volume deficit) | Hypervolemia (fluid overload) | |
|---|---|---|---|
| What's lost or gained | Water only | Fluid and electrolytes: blood volume drops | Too much water in the body |
| Causes | Diarrhea, vomiting, diuretics | Bleeding, GI (gastrointestinal) losses (nausea, vomiting, diarrhea), heavy sweating, large burns, diuretics, low fluid intake, increased urination | Commonly kidney problems (the kidneys balance salt and fluid) |
| Key findings | Early: dry nose and mouth, poor skin turgor, less urine. Then the heart beats faster and harder and vessels in the arms and legs constrict to save blood for the heart, brain and kidneys. | Quick weight gain, ↑ BP (blood pressure), bounding pulse, pale cool skin, edema, ascites, crackles, shortness of breath, neck vein distension | |
| Treatment | IV fluids (easiest), packed cells or blood transfusion | Get rid of the extra fluid: diuretics | |
If hypovolemia or dehydration go untreated
- Oliguria (decreased urine output)
- Tachycardia and palpitations
- Tachypnea (rapid breathing)
- Low BP; weak pulse; slow capillary refill
- Change in alertness or LOC (level of consciousness)
- Flattened neck veins
- Blue lips and nail beds
Hypovolemic shock: losing more than 20% of circulating blood volume. Without treatment, poor perfusion causes multiple organ failure (lungs, kidneys, brain and heart).
Skin turgor: skin that stays tented after you pinch and release it means fluid deficit.
Neck veins tell the story: flat when the tank is low (hypovolemia), bulging when it's overfull (hypervolemia).
Hct (hematocrit) and BUN rise with fluid deficit (hemoconcentration) and fall with overload (hemodilution). Older adults are at higher risk for both: less body water, a weaker thirst sense, and kidneys and heart that handle shifts less well. Skin turgor is less reliable in them.
| Fluid volume deficit (hypovolemia, dehydration) | Fluid volume excess (hypervolemia, overhydration) | |
|---|---|---|
| Vital signs | Tachycardia, thready pulse, low BP, orthostatic hypotension, fast breathing | Tachycardia, bounding pulse, high BP, fast breathing |
| Other findings | Thirst, dry mucous membranes, dry furrowed tongue, sunken eyes, no tears, cool clammy skin, acute weight loss, dizziness, confusion | Weight gain, pitting edema, distended neck veins, crackles, dyspnea and orthopnea (short of breath lying flat), confusion |
| Labs | Hct ↑ (but it drops if the cause is bleeding); BUN ↑; dehydration: sodium over 145, osmolality over 295, urine specific gravity over 1.030. A BUN-to-creatinine ratio over 20:1 means poor blood flow to the kidneys | Hct and BUN ↓; with water excess, sodium ↓ and osmolality under 280; urine specific gravity under 1.010; chest X-ray shows congestion |
| Causes ATI adds | NG suction, heavy sweating, fever, burns, diuretics, NPO (nothing by mouth) status, tube feedings without enough water | Heart failure, kidney failure, cirrhosis, too much sodium (diet, IV fluids, sodium bicarbonate antacids), SIADH (syndrome of inappropriate antidiuretic hormone: too much ADH holds on to water) |
| Nursing care | Oral rehydration first if the client can drink (drinks with electrolytes and glucose, like sports drinks); IV isotonic fluids for moderate or severe hypovolemia; daily weights; report urine under 30 mL/hr; check orthostatic BP; fall safety: change positions slowly, call light, help with walking | Semi-Fowler's; listen to all lung fields; oxygen as needed; daily weights; check edema (pretibial, sacral, around the eyes); slow the IV; diuretics; reposition at least every 2 hours and support swollen arms and legs |
Fluid restriction tips: remove the water pitcher, serve fluids in small cups so they look full, set short 1–2 hour goals, tell dietary staff and every shift how much the client may have, and record all oral intake.
Assessing fluid and electrolyte imbalances
- I&O
- Daily weight: same time, same scale
- Regular electrolyte labs
- Urine volume and concentration: low volume + high specific gravity = fluid volume deficit
Normal urine specific gravity: 1.005–1.030. It's checked more often than serum osmolality because it's easier to get, and it's the same idea (concentration) under a different name.
- 1.030 or higher = dehydration (concentrated urine)
- 1.005 or lower = fluid overload or renal failure (dilute urine)
Quick check
Which compartment holds most of the body's water?
Intracellular fluid, about 67%.
Dehydration vs hypovolemia: what's the difference?
Dehydration loses water but not sodium, so sodium and osmolality rise. Hypovolemia loses both fluid and electrolytes, so blood volume drops.
Urine specific gravity is 1.035. What does it suggest?
Dehydration (concentrated urine; 1.030 or higher).
Bounding pulse, crackles and distended neck veins. Which imbalance, and what treatment?
Hypervolemia (fluid overload); diuretics to remove the extra fluid.
What's the normal serum osmolality?
285–295 mOsm/kg.
Electrolytes
Sodium, potassium, calcium and magnesium: normal ranges, highs and lows, and what the nurse does.
What electrolytes do
Electrolytes are minerals that conduct electricity: they make muscles contract and let nerves communicate. They're in urine, blood, tissues and other body fluids, and also in food, drinks and supplements. They're measured on the CMP (comprehensive metabolic panel).
They're responsible for: balancing body water, balancing pH (acid-base), moving waste out of cells, moving nutrients in, and letting muscles, heart, nerves and brain work.
Causes of imbalance: dehydration, overhydration, certain medications, heart, kidney or liver disorders, and the wrong IV fluids or feedings.
One slide lists magnesium as 1.3–2.1 mg/dL, but the magnesium slides and ATI use mEq/L. This guide uses mEq/L.
- More normal ranges: chloride 98–106 mEq/L, phosphorus 3–4.5 mg/dL
- Sodium is the main electrolyte outside the cells (ECF); potassium is the main one inside the cells (ICF)
- Positive ions (cations): sodium, potassium, calcium, magnesium
- Negative ions (anions): chloride, phosphate, bicarbonate
- Highest risk for imbalances: older adults and clients with chronic illness or cognitive disorders
Sodium (Na+) 136–145 mEq/L
Supports nerve and muscle function, helps keep BP normal, and regulates fluid balance.
Hyponatremia (<136)
- Cause: loss of sodium or gain of water. Excess water is the most common cause; also vomiting, diarrhea, medications
- Nausea, confusion, lethargy, irritability
- Edema, muscle cramps, weakness
- Nursing: PO (by mouth) or IV sodium; possible fluid restriction
- Replace sodium slowly
Hypernatremia (>145)
- Cause: excess water loss or excess sodium intake. Water loss is the most common cause
- The CNS (central nervous system) is hit hardest: confusion, lethargy, agitation, irritability, hallucinations, delusions, possible seizures
- Nursing: encourage oral fluids; hypotonic IV fluids
Low sodium usually means too much water; high sodium usually means lost water. Sodium replacement has to be done slowly.
Both imbalances affect the brain because water shifts in or out of brain cells.
- Hyponatremia (brain cells swell): also caused by SIADH, heart failure, NG suction, tap-water enemas and diuretics. Headache, muscle twitching, decreased deep tendon reflexes, seizures. Fluid restriction for water excess; 3% saline only for severe cases. Change positions slowly; watch breathing if muscles are weak.
- Hypernatremia (brain cells shrink): also caused by fever, heavy sweating, burns, watery diarrhea, NPO status, hypertonic tube feedings. Thirst, dry sticky mucous membranes, warm flushed skin, fever, brisk reflexes, oliguria. Oral care to ease thirst, low-sodium diet, safety for confusion.
Potassium (K+) 3.5–5 mEq/L
Helps nerve and muscle cells work, especially the muscle cells of the heart.
Hypokalemia (<3.5)
- Cause: diuretics, GI loss
- First shows in skeletal muscles: weakness, leg cramps
- Fatigue
- Dysrhythmias
- Nursing: PO or IV potassium. IV potassium is a high-alert medication
Hyperkalemia (>5)
- Cause: kidney failure is common
- Nerve conduction and muscle contraction affected
- Paresthesia (numbness, tingling), paralysis
- Life-threatening dysrhythmias or cardiac arrest
- Nursing: sodium polystyrene sulfonate, IV insulin, dialysis
IV potassium: always diluted, on a pump, 10–20 mEq per HOUR. Never give it by IV push or bolus (it can stop the heart). One ATI page says "per minute"; your instructor confirmed in class that it's per hour.
Low K = Lasix (diuretics) and losses; high K = kidneys failing. Either way, watch the heart.
Foods high in potassium: baked potatoes, bananas, oranges, spinach, avocado, cantaloupe, salmon. Salt substitutes contain potassium, so clients with hyperkalemia should avoid them. Insulin pushes potassium into the cells, so check blood glucose (risk of hypoglycemia). Hypokalemia raises the risk of digoxin toxicity. Continuous ECG (electrocardiogram) monitoring for both.
| Hypokalemia | Hyperkalemia | |
|---|---|---|
| More causes | NG suction, vomiting, laxatives, corticosteroids, insulin, long runs of IV fluid with no electrolytes | Salt substitutes, blood transfusions, acidosis (diabetic ketoacidosis), burns and tissue injury, ACE (angiotensin-converting enzyme) inhibitors, potassium-sparing diuretics |
| ECG | Flat or inverted T waves, U waves, ST depression | Peaked T waves, wide QRS, prolonged PR |
| Muscles & gut | Weakness that climbs both legs and can reach the breathing muscles; hypoactive reflexes; constipation, ileus | Weakness and flaccid paralysis; diarrhea, cramping, hyperactive bowel sounds |
| Nursing | Treat the cause; oral or IV potassium; monitor urine output (kidneys must work before giving potassium), breathing, bowel sounds | Stop IV potassium and hold oral potassium; low-potassium diet; IV regular insulin with dextrose; sodium polystyrene sulfonate (by mouth or enema); loop diuretics if the kidneys work; dialysis if severe |
Calcium (Ca2+) 9–10.5 mg/dL
Keeps bones and teeth hard (where most of it is stored) and helps muscles move, nerves carry messages, and blood vessels move blood.
Hypocalcemia (<9)
- Cause: laxatives, lack of vitamin D, hormone changes in menopause
- Tetany!
- Numbness and tingling of fingers, mouth, feet
- Muscle cramps, seizures
- Can progress to spasm of the larynx
- Assess Trousseau's and Chvostek's signs
- Nursing: PO or IV calcium
Hypercalcemia (>10.5)
- Cause: cancers, hyperparathyroidism
- Nausea, vomiting, constipation
- Confusion, lethargy, slurred speech
- Chronic hypercalcemia → kidney stones
- Nursing: IV or PO medications
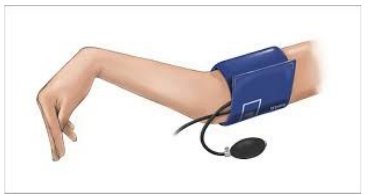
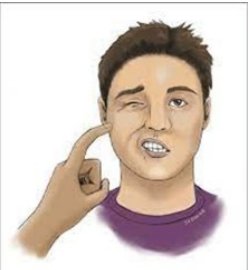
Low calcium = "twitchy." Calcium calms nerves, so without it nerves fire too easily: tingling, cramps, tetany, positive Trousseau's and Chvostek's. High calcium = "sluggish": constipation, lethargy, confusion.
Hypercalcemia: stones, bones, groans, moans (kidney stones, bone pain, abdominal groans like constipation and nausea, psychiatric moans like confusion).
- More hypocalcemia risks: thyroid or neck surgery (the parathyroid glands sit behind the thyroid), low magnesium, low albumin, many transfusions (the preservative in stored blood binds calcium), pancreatitis, kidney disease, long-term steroids, and acid-reducing medications.
- Ionized calcium (the active, unbound part, about half the total) is low under 4.5 mg/dL. It needs its own lab order; the CMP gives only total calcium.
- Hypocalcemia also brings hyperactive reflexes, prolonged QT on the ECG, and diarrhea. Nursing: seizure and fall precautions, emergency equipment nearby (laryngeal spasm), calcium and vitamin D. Calcium supplements absorb best in doses under 500 mg at a time.
- Hypercalcemia can also come from thiazide diuretics, lithium, too much vitamin D, and prolonged bed rest (bones release calcium). It brings decreased reflexes, thirst and polyuria. Nursing: more fluids, limit calcium, get the client moving, and watch for fractures.
Magnesium (Mg) 1.3–2.1 mEq/L
Helps regulate nerve and muscle function, BP and blood sugar, and helps make bone, protein and DNA.
Hypomagnesemia (<1.3)
- Cause: medications, decreased absorption, diarrhea
- GI: nausea, vomiting, decreased appetite
- Severely low: muscle spasticity, seizures
- Nursing: PO or IV magnesium
Hypermagnesemia (>2.1)
- Cause: kidney disease
- Dizziness, weakness, confusion
- Decreased DTRs (deep tendon reflexes)
- Nursing: IV or PO medications
Magnesium is a brake. Too much brake: everything slows (weak, dizzy, reflexes fade). Too little brake: nerves overreact (spasticity, seizures).
Low magnesium often comes with low calcium and low potassium, and can also cause positive Trousseau's and Chvostek's signs. High magnesium can slow breathing and heart rate; check reflexes and report absent ones. Calcium gluconate treats severe high magnesium (and protects the heart in high potassium).
- Hypomagnesemia causes: alcohol use disorder, diarrhea, diuretics, PPIs (proton pump inhibitors), malnutrition
- Hypomagnesemia signs: hyperactive reflexes, tremors, tetany, high BP, tachycardia, dysrhythmias. Oral magnesium can cause diarrhea.
- IV magnesium is a high-alert medication: double-check the dose with another nurse. Given too fast, it causes flushing, sweating and slowed breathing.
- Hypermagnesemia causes: kidney disease, and too many magnesium laxatives or antacids
- Hypermagnesemia check: the patellar reflex; absent = high magnesium
- Severe hypermagnesemia: slow, shallow breathing, bradycardia, low BP, cardiac arrest
- Hypermagnesemia treatment: stop magnesium sources; loop diuretics, calcium gluconate, dialysis if the kidneys can't clear it
All four at a glance
| Electrolyte | Low: main cause | Low: key sign | High: main cause | High: key sign |
|---|---|---|---|---|
| Sodium | Too much water | Confusion, nausea, edema | Water loss | CNS: agitation, hallucinations, seizures |
| Potassium | Diuretics, GI loss | Muscle weakness, leg cramps | Kidney failure | Dysrhythmias, cardiac arrest |
| Calcium | Laxatives, low vitamin D, menopause | Tetany, tingling, Trousseau's/Chvostek's | Cancers | Nausea, constipation, confusion |
| Magnesium | Meds, poor absorption, diarrhea | Nausea, vomiting; severe: spasticity, seizures | Kidney disease | ↓ deep tendon reflexes |
Quick check
A client's potassium is 6.0 mEq/L. What's the biggest danger?
Life-threatening dysrhythmias or cardiac arrest.
At what rate is IV potassium given?
10–20 mEq per hour, diluted, on a pump. Never IV push.
The BP cuff is inflated and the client's hand spasms. Which sign, and which imbalance?
Positive Trousseau's sign: hypocalcemia (latent tetany).
Most common cause of hyponatremia?
Excess water in the body.
A client with kidney disease has absent deep tendon reflexes. Which electrolyte?
Hypermagnesemia.
IV therapy & blood
IV solutions by tonicity, access devices, complications, and blood products.
IV solutions
- Colloids contain large molecules that can't pass through capillary membranes, so they stay in the vessels. Also called "plasma" or "volume" expanders.
- Crystalloids contain small particles that pass easily from the bloodstream into cells and tissues. Each is grouped by its tonicity: its ability to move water in or out of cells by osmosis.
| Tonicity | Osmolality vs blood | What happens to cells | Given for | Examples (slides) |
|---|---|---|---|---|
| Isotonic | Same | No fluid shift; no change inside cells | Increase ECF volume, maintain volume, treat hypovolemia; low blood volume from dehydration or bleeding | 0.9% normal saline, lactated Ringer's |
| Hypotonic | Lower | Water moves into cells; cells can swell | Correcting high serum electrolyte levels | 0.33% normal saline, 0.45% normal saline |
| Hypertonic | Higher | Water pulled out of cells into the vessels; cells can shrink | Low serum electrolyte levels, hypoglycemia | D5NS (dextrose 5% in normal saline), 3% and 5% sodium chloride, D10W (dextrose 10%), D5LR (dextrose 5% in lactated Ringer's) |
hypO = "Oh, cells swell" (water goes in). hypER = "cells shrivel" (water is pulled out). ISO = "I stay outside": it stays in the vessels and just adds volume.
The slides also list D5W (dextrose 5% in water) as isotonic, but your instructor said it isn't a focus for now.
- Hypotonic (0.45% saline): watch for low BP; avoid with burns, liver disease, trauma, or increased intracranial pressure (swelling brain cells make it worse).
- Hypertonic: watch for fluid overload; may be avoided with heart or kidney disease. D10W can irritate veins, so a central line is preferred.
- Lactated Ringer's: common for burns and trauma; use with caution in kidney failure.
- Colloids: albumin (natural; counts as a blood product) and synthetic dextran and hetastarch. They pull fluid into the vessels, so watch for fluid overload and allergic reactions. Albumin must finish within 4 hours of opening.
Vascular access devices
The slides name three kinds of IV access. They differ in how long the catheter is and where its tip ends up:
- Peripheral venous catheter (peripheral IV): short; tip in a small vein of the arm or hand
- Midline catheter: longer, but still in a peripheral arm vein
- CVAD (central venous access device): tip in a large central vein. Includes the PICC (peripherally inserted central catheter), central venous catheters, and the implanted port
Peripheral IV
- Single-lumen plastic catheter in a peripheral vein: hands, wrist, forearm, antecubital fossa
- Sizes 14 to 24 gauge: the bigger the number, the narrower the catheter
Larger gauges (16–18) for trauma, surgery, rapid fluids and blood; 20–24 for routine or fragile veins. Start distal on the nondominant arm. Avoid veins on the side of a mastectomy, an AV (arteriovenous) fistula, or recent infiltration. Clip hair; never shave. Insert bevel up at 10–30°. Older adults or clients on anticoagulants: use a BP cuff instead of a tourniquet and a smaller catheter.
Needlestick prevention: use needleless systems and safety devices, never recap, and drop needles in a sharps container right away.
Midline catheter
The slides only name the midline. In ATI, it's a longer peripheral catheter that can stay in place longer than a regular peripheral IV. The provider may consider a midline (or a CVAD) when therapy is expected to last more than about 5 days or the fluid irritates small veins. A short peripheral IV is enough for short-term therapy, such as fluids or medications for less than a week.
CVADs
CVADs are indwelling devices placed in a large central vein for blood products, medications, fluids and other therapy. They're used for clients who need frequent or long-term IV therapy. Types: tunneled and nontunneled, peripherally inserted, and implanted ports.
Don't get lost in the ATI detail on CVADs: keep it simple. The vein diagram on the slides is just a visual; you don't need to memorize it.
- PICC: put in through an arm vein; the tip sits in the vena cava
- Nontunneled central catheter: put straight into the jugular, subclavian or femoral vein
- Tunneled catheter: runs under the skin before entering the vein and can stay for years; keep scissors and other sharp objects away from it
- Implanted port: placed under the skin, usually on the chest, and accessed with a special noncoring needle
- CVADs are flushed with saline or heparin per facility policy to keep them from clotting. Clients who are unstable or getting intensive treatment such as chemotherapy may need one
Facility policy
- Peripheral IV site changed every 96 hr
- IV tubing: continuous infusion every 96 hr; intermittent infusion every 24 hr
- CVAD dressings changed every 7 days; Curos caps cover ports when not in use
IV complications
- Phlebitis / thrombophlebitis: inflammation of the vein (can be caused by a thrombus)
- Circulatory overload
- Infiltration (leak of IV fluid) or extravasation (damaging leak of a vesicant)
- VAD (vascular access device)-related infection
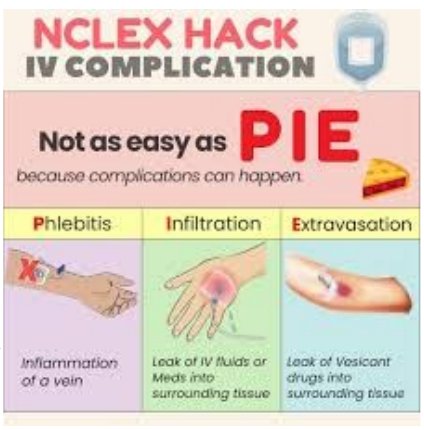
PIE: Phlebitis (inflamed vein), Infiltration (leak of IV fluid or meds into tissue), Extravasation (leak of a vesicant, a drug that damages tissue).
| Complication | Looks like | Do this |
|---|---|---|
| Phlebitis | Warm, red, painful; red streak or palpable cord along the vein | Stop the infusion and remove the catheter, elevate, warm compress, restart in the other arm |
| Infiltration | Cool, pale, swollen; slowed infusion; damp dressing | Stop and remove, elevate, warm or cold compress depending on the fluid, restart above the site or in the other arm |
| Extravasation | Same as infiltration, with a vesicant (can cause tissue death) | Stop, aspirate (don't flush), notify the provider (antidote may be needed) |
| Circulatory overload | ↑ BP, tachycardia, crackles, dyspnea, distended neck veins | Slow the IV, raise the head of the bed, vital signs and oxygen saturation, notify the provider, diuretics as prescribed. Prevent it: use a pump |
| Infection (cellulitis) | Pain, warmth, swelling, hardness, red streaking, pus, fever, chills | Stop and remove, culture the site and catheter, warm compresses 3–4 times a day, antibiotics as prescribed |
| Air embolism | Air enters the line | Prevent it: prime all tubing, change bags before they run dry, clamp a CVAD when changing tubing |
| Catheter embolus | Catheter tip missing on removal; pain if it travels | Tourniquet high on the arm, notify the provider, prepare for X-ray; save the catheter. Prevent it: never put the needle back into the catheter |
Phlebitis scale
| Grade | Findings (grade by the worst one present) |
|---|---|
| 0 | No symptoms |
| 1 | Redness at the site, with or without pain |
| 2 | Pain with redness and/or swelling |
| 3 | Pain with redness and/or swelling, streak, palpable venous cord |
| 4 | All of grade 3, plus a cord longer than 1 inch and pus (purulent drainage) |
Phlebitis is hot; infiltration is cold. Inflammation is warm and red; leaked fluid sitting in tissue is cool and pale.
Blood transfusions
Keep it simple from ATI.
| Product | What it is | Used for |
|---|---|---|
| Whole blood | WBCs, RBCs and platelets in plasma | Trauma and surgery with major blood loss |
| PRBCs (packed red blood cells) | Red cells (erythrocytes) with the plasma removed | Restore blood levels without much added volume |
| Plasma | The liquid part of blood that carries the cells | Replaces clotting factors and volume |
| Platelets | Thrombocytes: stop or prevent bleeding | Organ transplants, cancer treatment, surgery |
A blood type is the letter (A, B, AB or O) plus the Rh factor: positive (+) if the Rh protein is present, negative (–) if not. Matching matters because the immune system attacks red cells with markers it doesn't have.
| Client's type | Can receive red cells from | Can donate red cells to |
|---|---|---|
| O– | O– only | Everyone (universal donor) |
| O+ | O–, O+ | O+, A+, B+, AB+ |
| A– | A–, O– | A–, A+, AB–, AB+ |
| A+ | A–, A+, O–, O+ | A+, AB+ |
| B– | B–, O– | B–, B+, AB–, AB+ |
| B+ | B–, B+, O–, O+ | B+, AB+ |
| AB– | A–, B–, AB–, O– | AB–, AB+ |
| AB+ | Everyone (universal recipient) | AB+ only |
Most common: O+. Least common: AB–. O– is used in emergencies when the client's type isn't known yet.
To find who a client can receive from, check two things: (1) the letter: the same letter or O (AB takes any letter); (2) the sign: a negative client takes only negative blood, while a positive client takes either. Example: A+ → A or O, + or – → A–, A+, O–, O+.
- Consent first; 18–20 gauge IV already in place
- Two nurses check the unit against the client at the bedside
- Only 0.9% normal saline runs with blood
- Stay with the client the first 15 minutes (most reactions happen then); vital signs before, at 15 min, and per policy
- Finish within 4 hours
- Reaction (fever, chills, back pain, hives, dyspnea, low BP): stop the transfusion, keep the vein open with normal saline through new tubing, notify the provider, send the bag back to the blood bank
- Blood is typed and crossmatched first. PRBCs are usually given when Hgb (hemoglobin) drops to 7–8 g/dL; each unit raises Hgb about 1 g/dL and Hct about 3%
- Change blood tubing after every unit or every 4 hours. Never give IV medications through a line running blood
| Reaction | Clues |
|---|---|
| Acute hemolytic (wrong blood) | Fever, chills, low BP, pain in the chest, back or flank, red urine, shock |
| Febrile | Fever, chills, headache |
| Allergic | Itching, hives, flushing, wheezing (anaphylaxis: low BP, bronchospasm, shock) |
| Circulatory overload | Too much, too fast: high BP, distended neck veins, dyspnea. High-Fowler's and oxygen |
Quick check
Which IV fluid makes cells swell?
Hypotonic (0.33% or 0.45% normal saline).
A client is hypovolemic from bleeding. Which type of IV solution?
Isotonic: 0.9% normal saline or lactated Ringer's.
Which catheter is larger: 18 or 22 gauge?
18 gauge. The bigger the number, the narrower the catheter.
How often is tubing changed for an intermittent infusion?
Every 24 hours (continuous: every 96 hours).
The IV site is cool, pale and swollen. What's happening?
Infiltration.
Universal donor blood type?
O negative.
Acid-base balance & ABGs (arterial blood gases)
Keep it to the basics: the normal ranges and a three-step read of an ABG.
The basics
Acid-base balance is the right balance of acidic and basic (alkaline) compounds in the blood. Normal blood pH is 7.35–7.45.
Acidosis
- pH below 7.35
- Too much acid (or too little base)
Alkalosis
- pH above 7.45
- Too much base (or too little acid)
Acidosis and alkalosis aren't diseases; they result from many disorders. Each is respiratory or metabolic depending on the cause.
Acid: carbonic acid (CO2 + water)
- Controlled by the lungs
- Measured as PaCO2 (partial pressure of carbon dioxide)
Base: bicarbonate (HCO3–)
- Controlled by the kidneys: they make bicarbonate and hold on to it, and excrete hydrogen ions (acid)
Respiratory alterations
- Hyperventilation blows off CO2 (acid) → pH rises → respiratory alkalosis. Causes: anxiety, severe stress.
- Hypoventilation holds in CO2 (acid) → pH drops → respiratory acidosis. Causes: opioid overdose, pulmonary illnesses.
CO2 is the acid you breathe out. Breathe fast, lose acid (alkalosis). Breathe slow, keep acid (acidosis).
ABG cheat sheet
Know the ABG (arterial blood gas) ranges and basic interpretation. That's all you need for now.
| ABG value | Normal | Too low | Too high |
|---|---|---|---|
| pH | 7.35–7.45 | Acidosis | Alkalosis |
| PaCO2 (acid, lungs) | 35–45 mm Hg | Toward alkalosis | Toward acidosis |
| HCO3– (base, kidneys) | 22–26 mEq/L | Toward acidosis | Toward alkalosis |
| PaO2 (partial pressure of oxygen) | 80–100 mm Hg | Oxygenation, not acid-base | |
| O2 sat (oxygen saturation) | 95–100% | ||
- Look at the pH. Below 7.35 = acidosis. Above 7.45 = alkalosis.
- Look at the PaCO2. Is it out of range in the direction that explains the pH? If PaCO2 and pH move in opposite directions, it's respiratory.
- Look at the HCO3–. If HCO3– and pH move in the same direction, it's metabolic.
| Disorder | pH | PaCO2 | HCO3– |
|---|---|---|---|
| Respiratory acidosis | ↓ | ↑ | Normal |
| Respiratory alkalosis | ↑ | ↓ | Normal |
| Metabolic acidosis | ↓ | Normal | ↓ |
| Metabolic alkalosis | ↑ | Normal | ↑ |
ROME: Respiratory Opposite (pH and PaCO2 go opposite ways), Metabolic Equal (pH and HCO3– go the same way).
Practice reads
| pH | PaCO2 | HCO3– | Answer |
|---|---|---|---|
| 7.42 | 37 | 25 | Normal |
| 7.33 | 35 | 20 | Metabolic acidosis (pH low, HCO3– low, CO2 normal) |
| 7.49 | 32 | 24 | Respiratory alkalosis (pH high, CO2 low, HCO3– normal) |
| 7.30 | 52 | 24 | Respiratory acidosis (pH low, CO2 high) |
| 7.50 | 40 | 30 | Metabolic alkalosis (pH high, HCO3– high) |
Metabolic acidosis (diabetic ketoacidosis, diarrhea, kidney failure) brings deep, rapid Kussmaul breathing. Metabolic alkalosis comes from prolonged vomiting, gastric suction, or too many antacids.
The body compensates with the other system: the lungs respond in minutes to hours, the kidneys in hours to days. Kussmaul breathing is the lungs blowing off CO2 to raise the pH.
| Imbalance | Common causes | Look for | Nursing |
|---|---|---|---|
| Respiratory acidosis | Slowed breathing: opioids, sedatives, anesthesia, head or spinal cord injury; lung problems: pneumonia, atelectasis, COPD (chronic obstructive pulmonary disease), chest injury | Anxiety, confusion, sleepiness, shortness of breath | Airway and breathing first: lung sounds, oxygen, bronchodilators as prescribed |
| Respiratory alkalosis | Hyperventilation: anxiety, pain, fever, sepsis, head injury, pregnancy | Lightheadedness, dizziness, chest discomfort, tachycardia, confusion | Slow the breathing (coach, rebreathe into a paper bag for anxiety), treat pain or anxiety, fall precautions |
| Metabolic acidosis | Diabetic ketoacidosis, diarrhea, kidney or liver failure, starvation, lactic acidosis, aspirin (salicylate) overdose | Kussmaul breathing, headache, confusion, nausea, tachycardia | Treat the cause, IV fluids, sodium bicarbonate as prescribed |
| Metabolic alkalosis | Vomiting, NG suction, diuretics, antacids, hypokalemia | Muscle twitching, tingling, numb hands, lightheadedness, nausea; severe: seizures, dysrhythmias | Seizure and fall precautions, cardiac monitoring |
Nursing interventions
To prevent or correct fluid, electrolyte or acid-base imbalances: diet changes, changes to fluid intake, medications, IV therapy, blood and blood product replacement, parenteral nutrition, and client and family teaching.
Quick check
pH 7.31, PaCO2 50, HCO3– 25. Interpret.
Respiratory acidosis.
A client is having a panic attack and breathing fast. Which imbalance?
Respiratory alkalosis: hyperventilation blows off CO2.
Which organ controls bicarbonate?
The kidneys.
pH 7.32, PaCO2 40, HCO3– 18. Interpret.
Metabolic acidosis.
What does an opioid overdose do to the ABG?
Hypoventilation retains CO2: respiratory acidosis.
Nutrition
Nutrients, energy, labs, assessment, therapeutic diets, and keeping clients safe while they eat.
Principles & digestion
Nutrition is the study of food, how it affects health, and how the body turns it into energy. Adequate nutrition is essential for wellness.
6 classes of nutrients
- Supply energy: carbohydrates, proteins, lipids (fats)
- Regulate body processes: vitamins, minerals, water
Macro vs micro
- Macronutrients (protein, carbs, fat): eaten in large amounts; the building blocks of the diet; provide energy
- Micronutrients (vitamins, minerals): only small amounts needed
Digestion breaks food down into simple substances that are absorbed as nutrients or eliminated as waste.
| Organ | Job |
|---|---|
| Esophagus | Muscles push food down to the stomach |
| Stomach | Holds and digests food with acids and enzymes |
| Liver | Filters toxins; makes bile to break down carbs, proteins and fats (metabolism) |
| Gallbladder | Stores bile and releases it when needed |
| Pancreas | Makes insulin for sugar metabolism |
| Small intestine | Breaks food down and absorbs most nutrients |
| Large intestine | Removes water and electrolytes; forms feces |
| Rectum | Temporary storage for feces |
| Anus | Expels feces |
Digestive issues: stress, diet and disease can disrupt digestion, causing diarrhea, constipation, indigestion, food poisoning, flatulence and acid reflux.
Energy balance & metabolism
The average person needs about 2,000 calories a day to maintain their weight.
- Calories are the energy stored in food, used for walking, breathing and thinking
- Calories in must equal calories burned. Too few = undernourished; too many = obesity
- Basal metabolism: energy for the body's involuntary activities at rest (the body still needs calories at rest)
- Men usually have a higher BMR (basal metabolic rate) because of more muscle mass
- Increase BMR: growth, infection, fever, emotional stress, extreme temperatures, some hormones (healing increases the body's work)
- Decrease BMR: aging, prolonged fasting, too little sleep
No more than 35% of calories should come from fat. Extra glucose is stored as glycogen in the liver and muscles as backup energy. A healthy weight-loss pace is 1–2 lb a week, and losing just 5–10% of body weight improves BP, blood glucose and cholesterol. Adults need 150 minutes of moderate activity a week plus 2 days of muscle strengthening.
Energy nutrients
| Nutrient | Key points |
|---|---|
| Carbohydrates | Primary fuel source (including the brain and nervous system); 45–65% of daily calories; sugars and starches; digested faster than protein or fat; converted to glucose. Complex carbs = slow, steady energy; simple carbs = quick spike |
| Proteins | "Building block of the body": growth, healing, maintenance; forms all body structures; secondary energy source (used if carbs run out). Enough protein prevents muscle breakdown, pressure injuries and muscle wasting |
| Lipids (fats) | 95% are triglycerides. Help absorb vitamins, give energy, insulation, structure and temperature control; part of every cell membrane. Most animal fats are saturated; most vegetable fats unsaturated |
"Bad" fats
- Trans and saturated
- Raise cholesterol → heart disease, stroke
"Healthy" fats
- Monounsaturated (avocado, olive oil)
- Lower cholesterol; omega-3s (fish oil) support the brain
Nutrition labs
| Lab | Normal | What it tells you |
|---|---|---|
| Total cholesterol | <200 mg/dL | High = atherosclerosis, heart disease, stroke risk |
| HDL (high-density lipoprotein) "good" | Female >55 · Male >45 mg/dL | The only one we want high |
| LDL (low-density lipoprotein) "bad" | <130 mg/dL | Keep low |
| Albumin | 3.5–5 g/dL | Nutrition status a few weeks before the draw |
| Prealbumin | 19–38 mg/dL | Short-term (current) nutrition; excellent malnutrition marker; more reliable than albumin |
HDL = Happy, keep it High. LDL = Lousy, keep it Low. Prealbumin is the present; albumin is the past few weeks.
Vitamins, minerals & water
You don't need the specifics of each vitamin, but know the types and what they do for the body. You don't need to memorize the mineral chart.
Vitamins are organic compounds needed in small amounts for metabolism of carbs, proteins and fat. Fresh foods have more than processed ones, because light, heat, air and preparation destroy vitamins.
Water-soluble: B & C
- Absorbed straight into the bloodstream
- Not stored: extra leaves in the urine, so the body needs a steady supply and a deficiency shows up sooner
Fat-soluble: A, D, E, K
- Absorbed with fat into the lymph, then carried on proteins
- Stored in the liver and fat, so too much can build up to toxic levels
What each vitamin does
| Vitamin | What it does for the body | Why it matters for nursing |
|---|---|---|
| B (B complex) water-soluble | Helps with energy, brain function and cell metabolism | Clients with alcohol use disorder often run low on B vitamins, which shows up as fatigue and confusion |
| C water-soluble | Needed to make collagen (the protein in skin, gums and healing wounds); an antioxidant; supports immune function; helps the body absorb iron | Needed for wound healing. Too little causes swollen, bleeding gums and slow healing |
| A fat-soluble | Affects vision (visual acuity), the skin and mucous membranes, and immune function | Helps wound healing and infection defense. Because it's stored, too much can be toxic |
| D fat-soluble | Needed for calcium and phosphorus metabolism; helps the body absorb calcium | Low vitamin D leads to low calcium and bone loss, a special concern for older adults |
| E fat-soluble | An antioxidant that protects vitamin A; helps fight infection | Part of protecting cells and fighting infection |
| K fat-soluble | Helps make the proteins needed for blood clotting | The antidote for warfarin. Clients on warfarin keep their vitamin K intake steady. Too little vitamin K means easy bleeding and bruising |
Fat-soluble vitamins "ADEK" stick around in fat; B and C "wash out" with water. C is for collagen (healing); K is for clotting; D is for bones (it brings in calcium).
Minerals (inorganic; usually carry a + or – charge) help hydration, metabolism, fluid regulation, nerve impulses, energy, and healthy bones, teeth and blood. Processing doesn't usually destroy them unless food is overcooked or soaked. They're mostly absorbed in the small intestine. Iron carries oxygen (hemoglobin).
Water: an essential nutrient
- 50–60% of body weight; two-thirds of it is inside cells (ICF)
- A solvent for chemical processes; helps digestion, absorption, circulation and excretion
- Regulates temperature through sweat evaporation; isn't stored
- Intake usually equals output
Average adult water intake: 2,500–3,500 mL/day.
Supplements don't replace a healthy diet, and the FDA (Food and Drug Administration) doesn't approve them before they're sold. Ask about them in every nutrition assessment, and clients should check with their provider first.
- St. John's wort weakens birth control, heart medications and antidepressants
- Vitamin K weakens warfarin (raises clot risk); keep vitamin K intake steady
- Antioxidant supplements (vitamins C and E) can weaken chemotherapy
- Too much iron: nausea, vomiting, liver damage. Too much vitamin A: headaches, weaker bones
Guidelines, labels & factors
Dietary guidelines
- Variety of nutrient-rich foods (natural sources beat supplements)
- Balanced eating pattern
- Limit saturated fat, trans fat, cholesterol, added sugar, salt, alcohol
- Healthy weight; stay active
- Drink enough water
Other terms
- Calorie density: calories per volume or weight of food
- Glycemic index: how fast a food raises blood glucose. High = rapid spike ("roller coaster"); low = slow, steady
Food labels: serving size, calories, % Daily Value, breakdown of nutrients. Reading labels lets nurses help clients choose better.
Don't assume a client can read a food label (for example, without their glasses). Ask whether they need help.
Factors that affect nutrition: physical factors, illness or trauma (healing), medications, megadoses of supplements (can affect other processes), alcohol use disorder (toxic to the GI tract; B vitamins are needed to absorb it), social determinants of health and money (food deserts), and culture, religion and traditions.
Ask the client about these factors instead of assuming: whether they can afford food, whether they can get to a grocery store, and any cultural or religious food practices.
- Everything on the label is per serving. Eat two servings, double every number.
- %DV (percent Daily Value): 5% or less = low, 20% or more = high. Choose high %DV for fiber, vitamin D, calcium, potassium and iron; low %DV for sodium, added sugars and saturated fat.
- Added sugars are counted inside total sugars.
- Net carbs = total carbohydrates − fiber (and sugar alcohols). 10 g carbs with 5 g fiber = 5 g net carbs.
- Sodium: no more than 2,300 mg a day (about 1 teaspoon of salt) for healthy adults, less with heart disease. About 70% comes from processed and restaurant food.
- Fiber: women 19–30 need 28 g a day, men 19–30 need 34 g; needs go down with age.
Growth stages: adolescence, pregnancy and lactation raise needs; activity raises needs; needs level off in adulthood, and adults need fewer calories as BMR drops.
Older adults
- Slower metabolism → fewer calories
- Thirst sense fades → dehydration risk
- Need the same vitamins and minerals as younger adults; supplements may be needed
- Calcium needs rise (absorption drops) for men and women
- Need fiber and bulk for GI function
- Less absorption of vitamins and minerals; less insulin production and sensitivity
BMI & malnutrition
| BMI (body mass index) | Category |
|---|---|
| Under 18.5 | Underweight |
| 18.5–24.9 | Normal |
| 25–29.9 | Overweight |
| 30 or higher | Obese |
| Over 40 | Extreme obesity |
Know the normal BMI range. Muscle weighs more than fat, so muscular clients can have a falsely high BMI.
Two-thirds of adults are overweight or obese, which is tied to several chronic diseases. Low intake: anorexia (lack of appetite).
BMI = weight (kg) ÷ height (m)². Example: 80 kg and 1.6 m tall → 1.6 × 1.6 = 2.56 → 80 ÷ 2.56 = 31.3 (obese).
In pounds and inches: weight ÷ height ÷ height × 703. Example: 170 lb, 64 in → 170 ÷ 64 ÷ 64 × 703 = 29.2 (overweight).
Malnutrition: impaired development or function from a long-term deficiency, excess or imbalance of nutrients. Signs: less activity, weight loss, reduced height, hair loss, swelling or a bigger abdomen. Malnourished clients heal slower and have more complications.
Hair and nails go first: the body sacrifices them when nutrients run short. No protein → low albumin → fluid leaks out of the vessels → edema.
Signs of poor nutrition: dry, brittle hair and nails; dry, scaly skin; loss of fat under the skin; flaccid muscles, weakness and fatigue; swollen or bleeding gums; dry, dull eyes; poor posture; mental status changes; changes in weight and bowel pattern; frequent infections. Low vitamin C → irritated gums.
| Eating disorder | Key features |
|---|---|
| Anorexia nervosa | Very low body weight, fear of gaining weight, sees self as fat, restricts food |
| Bulimia nervosa | Binge eating, then purging (vomiting, laxatives, diuretics, overexercise, fasting), at least weekly for 3 months |
| Binge-eating disorder | Binges with loss of control, then guilt or shame; no purging; often overweight |
Purging by vomiting, laxatives or diuretics ties back to this week: low potassium and fluid volume deficit.
Nutritional assessment
- 24-hour food recall
- Food frequency questionnaire
- Chewing, swallowing, condition of teeth
- Appetite, allergies, diet
- Current illness, medical and surgical history, labs
- Income and food budget
- Medical, social, economic information
- Past and current drugs; drug dependence or misuse
- Age, gender, family history, lifestyle
- Occupation, exercise, sleep
- Religious or cultural considerations
Therapeutic diets
| Diet | What it is | Who it's for & notes |
|---|---|---|
| Regular | Healthy foods from all food groups | No special needs; no restrictions |
| Clear liquid | See-through: water, tea, coffee, broth, carbonated drinks, popsicles, gelatin, clear fruit juices | Before or after surgery and some tests, or while the GI tract recovers from vomiting or diarrhea. Fluids and some electrolytes; minimal digestion; leaves almost no residue; reintroduces the GI tract slowly; short-term (not true nutrition). No red dye: it can look like blood |
| Full liquid | All clear liquids plus anything pourable at room temperature: milk, soups, pudding, yogurt, custard, plain frozen desserts, vegetable juices | The step up from clear liquids, such as after abdominal surgery; oral or facial surgery; can't chew solid food |
| Soft | Foods that are soft and easy to swallow and digest. Leaves out most raw fruits and vegetables, seeds, nuts and dried fruit | Trouble chewing (no teeth or dentures) or swallowing; after jaw, mouth or abdominal surgery; can be long-term |
| Pureed | Soft, smooth, no chewing needed | Dysphagia (difficulty swallowing) or trouble chewing; recent oral surgery; numbness in the mouth |
| NPO (nothing by mouth) | No food or drink | Before surgery or a test that needs an empty stomach, or when the client can't swallow safely. May allow meds with small sips of water, unless fully NPO; restarting food needs a provider's order |
| Heart healthy | Limit sodium and unhealthy fat | High blood pressure, heart disease, high cholesterol. Less sodium means less fluid held in the body, which helps heart failure and fluid overload |
| Renal | Limit sodium, potassium, phosphorus | Kidney disease: damaged kidneys can't clear these, so they build up in the blood |
| Consistent carbohydrate | Controls carb intake | Diabetes: about the same amount of carbohydrate at each meal keeps blood glucose steady and matches diabetes medications |
| High-fiber | Whole grains, fruits | Prevents constipation and hemorrhoids; lowers cholesterol; helps control blood glucose; lowers the risk of colorectal cancer, heart disease, obesity and type 2 diabetes. Drink plenty of fluids with it |
| Low-residue | Easy to digest, low fiber | Less stool and less work for the bowel: diarrhea, a bowel flare-up, before and after bowel procedures or surgery |
Clear = can see through it. Full = can pour it. Renal = "SPP": limit Sodium, Potassium, Phosphorus.
- NPO means nothing at all, not even ice chips; clarify with the provider whether medications are allowed. Restarting food needs a provider's order.
- Mechanical soft: diced or ground foods. Dysphagia diet: pureed food and thickened liquids.
- Low sodium: no added salt, or 1–2 g sodium a day. Low cholesterol: no more than 300 mg a day.
- Diabetic: balanced protein, fat and carbohydrate, about 1,800 calories.
- The nurse's job: make sure the client gets the prescribed diet and help advance it as ordered.
Ways to limit sodium
- No table salt; don't salt food while cooking
- Avoid processed meats (lunch meat, hot dogs, bacon, sausage)
- Choose "no salt added" foods
- Avoid soups unless low sodium, and only one serving
- Read labels for sodium per serving
Nausea & appetite
Nausea
- Assess the cause and for dehydration
- Tissues and cool water or ice at the bedside
- Sights and smells worsen nausea: remove food that won't be eaten right away; avoid strong perfumes; fresh air
- Oral care
- Small, frequent, non-greasy meals
- Antiemetics PRN (as needed)
Stimulating appetite
- Frequent small meals; offer preferred foods
- Help with oral hygiene
- Limit liquids with meals (offer them between meals so the client eats more food)
- Clean, dry environment
- Meals with friends or family
- Comfortable position, pain controlled, no unnecessary interruptions at mealtime
Aspiration
Dysphagia (difficulty swallowing) or being unable to swallow raises aspiration risk.
Overt aspiration
- Obvious signs: coughing, wheezing, trouble breathing, congestion, gagging, throat clearing, vomiting
Silent aspiration
- No obvious signs
Preventing aspiration
- Upright, preferably in a chair, while eating
- In bed: head of bed at 90° to eat, and at least 45° for 1 hour after
- Cut food into small bites; don't rush or force feeding
- No straws
- Check the mouth for pocketed food after eating
- Watch for signs of aspiration during the meal
- Monitor LOC; avoid sedatives and hypnotics before meals
- Remind the client to tuck their chin to swallow
- Speech therapy consult for a swallow evaluation (may change the diet or add thickened liquids)
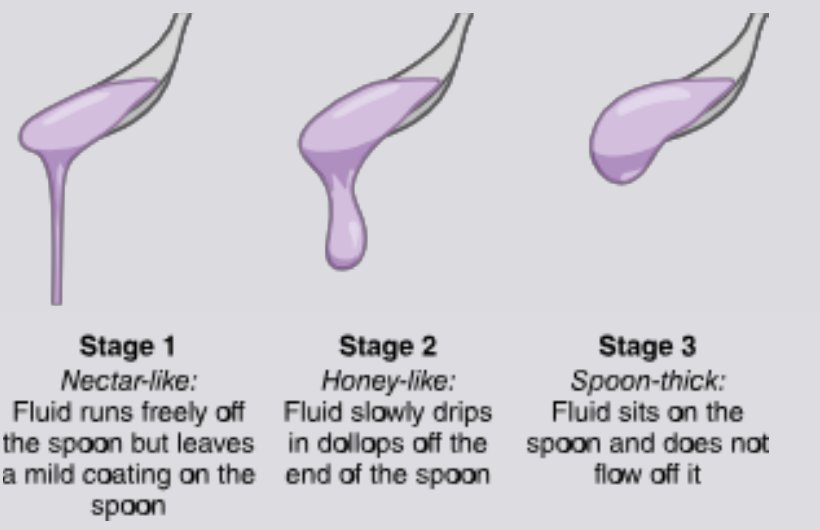
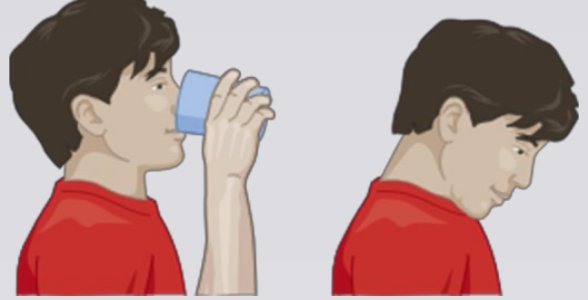
Thin liquids slip into the airway. The thicker the liquid, the slower it moves, and the more time the client has to swallow safely.
Assisting with eating
- Sit at eye level
- Appropriate drinks; cut food into small pieces
- Involve the client: preferences, order of foods, condiments
- Restroom used? Hands washed? Dentures in?
- Napkin over clothes; adaptive utensils as needed
Taught by a speech therapist after a swallow evaluation. Risk factors for aspiration: stroke, acid reflux, mouth sores, dental problems.
| Technique | How |
|---|---|
| Chin tuck | Chin down to the chest while swallowing; narrows the airway entrance |
| Turn the head to the weak (affected) side | Closes off the weak side so food goes down the strong side |
| Tilt the head to the strong side | Gravity moves food down the strong side |
| Supraglottic swallow | Hold the breath, swallow (up to 3 times), then cough to clear what's left |
| Mendelsohn maneuver | Swallow, hold the swallow 2–3 seconds, finish, relax |
Also: support the head, neck and upper back; watch for coughing, choking, gagging and drooling; oral care after meals and snacks.
Foods to know
Every specific food named in the slides and the ATI material, grouped by what it's high in or which diet it fits. Most of these lists come from ATI rather than the slides. They're handy for client-teaching questions ("Which food should the client choose?").
Electrolytes
| High in | Foods | Teach for |
|---|---|---|
| Potassium | Baked potato, prune juice, plain nonfat yogurt, white beans, sweet potato, banana, spinach, salmon, avocado, oranges, cantaloupe, dark leafy greens | Add for hypokalemia; limit for hyperkalemia and kidney disease |
| Sodium | Roasted ham, frozen shrimp, frozen pizza, canned soup, vegetable juice, cottage cheese, instant pudding, soy sauce, lunch meat, hot dogs, bacon, sausage | Limit for hypernatremia and on low-sodium, heart-healthy and renal diets |
| Calcium | Cheese, plain nonfat yogurt, almond milk, calcium-fortified orange juice and cereals, soymilk, milk, broccoli, leafy greens, legumes, almonds | Add for hypocalcemia and bone health; limit for hypercalcemia |
| Magnesium | Cooked spinach, pumpkin seeds, black beans, soybeans, cashews and other nuts, dark chocolate, avocado, tofu, salmon, banana | Add for hypomagnesemia; limit for hypermagnesemia and kidney disease |
Lower-sodium swaps: fresh shrimp instead of frozen, low-sodium vegetable juice, regular (not instant) pudding, "no salt added" canned foods. Salt substitutes usually contain potassium: avoid them with hyperkalemia or kidney disease.
Energy nutrients
Carbohydrates
- Healthy: whole-grain bread, brown rice, baked potatoes, fruits, vegetables, legumes
- Empty calories: cookies, chips, sweetened drinks, processed foods
Protein
- Complete: beef, poultry, fish, eggs, whole milk
- Other: beans, soy, nuts
Fats
- Healthy: olive oil, avocado, salmon, nuts; omega-3s in fish oil, walnuts, flaxseed
- Saturated: cheese, butter, whole milk, most animal fat
- Trans: processed foods with partially hydrogenated oils
Vitamins & minerals
| Nutrient | Foods |
|---|---|
| Vitamin C | Citrus, strawberries and berries, tomatoes, Brussels sprouts, spinach, potatoes |
| Vitamin K | Spinach, kale, parsley, liver, butter (keep intake steady on warfarin) |
| Vitamin D | Fish oil, milk, eggs, dairy, and sunlight |
| Vitamin A | Fish liver oil, beef liver, dairy, green leafy vegetables, sweet potatoes |
| Vitamin E | Almonds, wheat germ, sunflower seeds, spinach |
| Folate (B9) | Leafy greens, orange juice, eggs, beans, avocado |
| Vitamin B12 | Clams, beef, salmon, milk, yogurt |
| Iron | Organ meats, red meat, leafy greens, iron-fortified foods |
| Zinc · Iodine · Phosphorus | Zinc: meats, fish, whole grains · Iodine: seafood, iodized salt, dairy · Phosphorus: eggs, fish, poultry, milk |
Fiber & blood glucose
High fiber
- Whole grains: bran flakes, barley, oatmeal, oat bran muffin, brown rice, whole-wheat spaghetti, whole-wheat bread, rye bread, air-popped popcorn
- Legumes: lentils, black beans, lima beans, baked beans, split peas, green peas
- Fruit: raspberries, strawberries, pears and apples with skin, bananas, oranges, dried figs, raisins
- Vegetables: broccoli, Brussels sprouts, artichoke, turnip greens, sweet corn, carrots, potato with skin, tomato paste
- Nuts: almonds, pistachios, pecans
Low residue (low fiber)
- Dairy (custard, yogurt), eggs, ripe bananas
- Avoid anything high in fiber, such as whole grains (barley, oats), legumes (lentils, black beans), raw or gas-producing vegetables (raw broccoli, cabbage), nuts, seeds and fruit skins
Glycemic index
- High: potatoes, white bread, processed snacks; pictured on the slide: bread, cake, watermelon, beer, doughnuts
- Medium (slide picture): papaya, banana, croissant, coconut, beet, pumpkin
- Low: legumes, vegetables, fruits, whole grains; pictured: oranges, tomatoes, broccoli, blueberries, strawberries, avocado, plums

Foods by diet
| Diet | Foods |
|---|---|
| Clear liquid | Water, tea, coffee, broth, carbonated drinks, popsicles, gelatin, pulp-free clear juice, sports drinks. No red dye (red popsicles or gelatin): it can look like blood |
| Full liquid | All clear liquids plus milk, strained soups, pudding, yogurt, custard, ice cream, milkshakes, vegetable juice |
| Soft | Well-cooked vegetables, low-fiber cereal, tender meat or fish, pancakes, creamy peanut butter, cooked fruit without skin or seeds |
| Pureed | Pudding, mashed potatoes, yogurt, pureed meats, broth, ice cream |
| Renal: limit potassium |
|
| Renal: limit phosphorus |
|
| Heart healthy | Fruits, vegetables, whole grains, lean meats, fish, skim milk, no-salt-added canned foods |
| Food or nutrient | Health problem it's tied to |
|---|---|
| Potassium-rich foods | Add for hypokalemia. Limit in kidney disease: high potassium causes dysrhythmias and raises heart attack risk |
| Phosphorus foods (renal diet) | Failing kidneys can't clear phosphorus; high phosphorus pulls calcium out of the bones → bone disease and fractures |
| Sodium, processed and fast food | Hypertension and heart disease. Fast food is calorie dense and high in sodium and fat → weight gain and cardiovascular disease. "Healthy" snacks like granola bars, trail mix and baked chips can hide sodium and sugar |
| Saturated and trans fats | Raise LDL; trans fats also lower HDL → heart disease and stroke |
| Whole grains | Lower the risk of heart disease, stroke and diabetes; help lower cholesterol and weight |
| Fiber | Lowers cholesterol and helps control blood glucose; lowers the risk of constipation, hemorrhoids, colorectal cancer, heart disease, hypertension, obesity, stroke and type 2 diabetes; keeps you full longer |
| Added sugars, sweetened drinks | Dental caries (cavities) |
| Broth for vomiting or diarrhea | Replaces sodium but not enough water, so dehydration can continue. Drinks with electrolytes and glucose (sports drinks) come first for oral rehydration |
| Overeating, inactivity (obesity) | Diabetes, high BP, some cancers, osteoarthritis, high cholesterol. Clients with obesity can still be malnourished if their food is low in nutrients |
Fasting glucose (nothing by mouth for at least 8 hours): 74–106 mg/dL. Two hours after a meal, blood glucose should be back under 140 mg/dL.
Hypoglycemia (glucose under 70 mg/dL): give something with sugar that raises glucose quickly (glucose tablets or gel, regular soda, juice, honey, or hard candy), recheck in 15 minutes, and repeat until it's at least 70. Then a meal or snack.
Check glucose before giving insulin. Inject at 90° (45° if the client has little fat under the skin), at least 2 in from the navel, away from scars or bruised, lumpy or numb skin.
Quick check
Which lab best shows current (short-term) nutrition?
Prealbumin (19–38 mg/dL).
Which vitamins can build up to toxic levels?
Fat-soluble: A, D, E and K (stored in the liver and fat).
Is pudding allowed on a clear liquid diet?
No. Pudding is full liquid; clear liquids are see-through.
Which three minerals does a renal diet limit?
Sodium, potassium and phosphorus.
How long should a client at risk for aspiration stay upright after eating?
At least 1 hour, at 45° or higher.
Normal BMI range?
18.5–24.9.
Name three foods high in potassium.
Any three: baked potato, banana, spinach, salmon, avocado, oranges, prune juice, white beans, yogurt.
Enteral & parenteral nutrition
When a client can't eat enough: feeding tubes, checking placement, giving feedings, and TPN.
Enteral nutrition & tube types
Enteral nutrition puts formula directly into the GI tract through a tube. It can give total or supplemental nutrition, short or long term.
| Tube | Path | Use |
|---|---|---|
| NG (nasogastric) | Nostril → esophagus → stomach | Short-term |
| Nasoduodenal | Nostril → past the stomach → duodenum | |
| Nasojejunal | Nostril → stomach → jejunum (small intestine) | |
| G-tube (gastrostomy) / PEG (percutaneous endoscopic gastrostomy) | Through the abdominal wall directly into the stomach | Long-term; PEG is the most common placement |
| J-tube (jejunostomy) | Through the abdominal wall directly into the jejunum | Long-term (on the slide's feeding-tube diagram) |
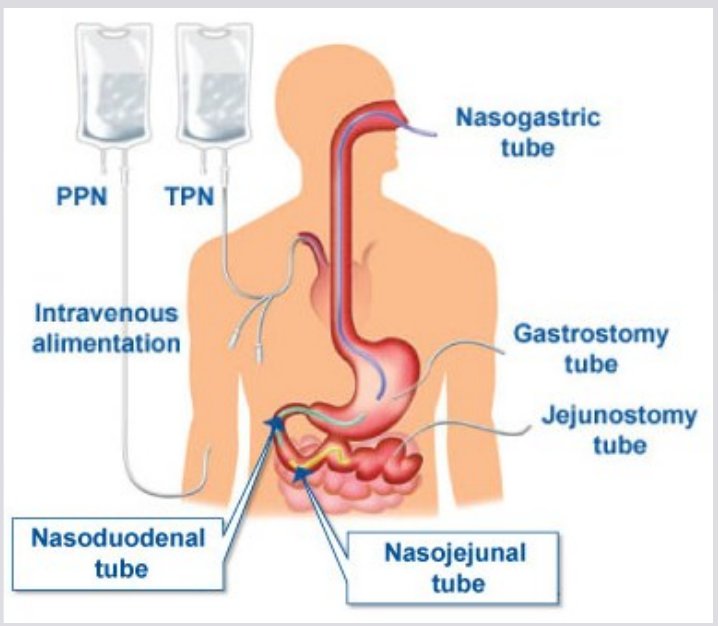
The name is the route: "naso-" starts in the nose, "-gastric" ends in the stomach, "-jejunal" ends in the jejunum. Anything with "-ostomy" goes through the skin and is long-term.
Nasal tubes are for under about 4 weeks. Small-bore feeding tubes are 8–12 French for adults; large-bore tubes (12–18 French) are for suction, lavage (washing out the stomach) and decompression.
Enteral feeding is preferred over parenteral: fewer infections and shorter hospital stays. It's not used with GI bleeding, bowel obstruction, or a bowel without enough blood flow. A client is NPO at least 8 hours before a G-tube is placed.
Checking tube placement
Verify placement of nasogastric, nasoduodenal and nasojejunal tubes after insertion, before every feeding or medication, and at regular intervals during continuous feedings.
X-ray (radiographic) verification is the gold standard. Placement is confirmed by X-ray before the first feeding or medication. Other checks: tube length and marking, aspirate pH, and how the aspirate looks.
- Check the tube's mark at the nares
- Disconnect from feeding or suction
- Instill 30 mL of air to clear the tube
- Aspirate to check gastric residual; return it if less than 100 mL
- Check pH: gastric contents about 1–4 (the ATI NG chapter accepts 5.5 or less)
- Flush with 30 mL of water when finished
- Medications: flush 30 mL of water before and after
- Cap or clamp the tube when not in use; change tubing every 24 hours
Don't rely on listening over the stomach while pushing air: you can hear air even if the tube is in the lung. Capnography (CO2 detection) means the tube is in the airway: remove it. No fluid? Turn the client side to side and try more air.
Extra risk of a misplaced tube: decreased LOC, weak cough or gag, recently removed breathing tube, agitation.
Giving enteral feedings
Continuous
- Gradual, steady delivery
- Requires a feeding pump
Intermittent (bolus)
- Equal portions at regular times
- Pump, gravity, or syringe
- Flush with water after each bolus
- Check tube placement first
- Client upright: head of bed 30–45° during feedings, and at least 30° for 1 hour after
- Watch for feeding intolerance: gastric distention, abdominal discomfort, nausea, vomiting, diarrhea, reflux
- Change the system and tubing every 24 hours
Complications
- Aspiration
- Clogged tube: crush medications thoroughly and flush
- Nasal erosion or pressure injury
- Diarrhea
- Nausea, vomiting, abdominal distension
- Dislodgement
- Infection at the gastrostomy site
Check residuals every 4–6 hours for tubes in the stomach; return the residual unless it's large (over 250 mL: follow protocol). Use a 50–60 mL syringe on small-bore tubes (smaller syringes can collapse them). Hang only 4 hours of formula at a time (the NG chapter says to follow the manufacturer's hang time and to discard refrigerated unused formula after 24 hours); formula at room temperature; wipe the can top with alcohol; label the bag and tubing. Check blood glucose every 4–6 hours until the full rate is tolerated for 24 hours. Don't delegate tube feedings. Flush with water before and after each intermittent feeding, every 4 hours during continuous feeds, and after medications and residual checks. The skills module allows 30–50 mL; the flagged steps above use 30 mL. Listen for bowel sounds first as a baseline (absent sounds alone don't stop a feeding).
| Formula | For |
|---|---|
| Polymeric (whole nutrients) | Clients who can digest and absorb whole nutrients |
| Modular | One nutrient (protein, fat, glucose) added to supplement; not complete nutrition |
| Elemental (predigested) | A partly working GI tract |
| Specialty | Specific illnesses: liver failure, lung disease, diabetes |
Schedules: intermittent (bolus, by syringe or pump), continuous (pump only), or cyclic (a set block each day, such as 2100 to 0900).
- Most common complications: displaced tube, aspiration, diarrhea
- Diarrhea: ask about a slower rate, diluting or changing the formula, fiber, or lactose-free formula; keep the formula and tubing clean
- Skin: protect the nose with a skin adhesive under the tape and shift the tube's position often
- Feelings: tube feeding can bring isolation and body-image worries; offer privacy or company during feedings, listen, and teach the family
More from the NG tube chapter
NG tube uses: decompression, feeding, lavage (washing out the stomach for bleeding or poisoning), and compression (a balloon to stop bleeding).
Tube duration: nasal tubes short-term; surgical gastrostomy or jejunostomy for more than about 6 weeks; PEG or PEJ (endoscopic) for more than 30 days. Intestinal placement is preferred with gastroparesis, reflux or past aspiration pneumonia.
Complications: suspected aspiration → stop the feeding first, turn to the side, suction, oxygen, notify, chest X-ray. Diarrhea 3+ times in 24 hours → slow the rate, notify, dietitian, skin care, ask about antibiotics. Nausea → slow the rate, head of bed 30°, room-temperature formula, turn to the side, check patency and residual.
NG comfort: sore nares → water-soluble lubricant, try the other nostril; dry mouth → rinses, lozenges, oral care; not draining → irrigate per protocol, reposition, check the suction.
NG tubes: insertion, suction & removal
For an NG tube going into the stomach: measure from the tip of the nose → earlobe → xiphoid process, then add 10 cm.
ATI measures nose → earlobe → xiphoid process and stops there. This guide follows the extra 10 cm your instructor gave.
Insertion
- Check the order, nares and gag reflex; agree on a stop signal; suction at the bedside
- High-Fowler's position
- Measure nose tip → earlobe → xiphoid process and mark it (add 20–30 cm for duodenal or jejunal tubes)
- Water-soluble lubricant; advance toward the back of the throat, then head tilted forward (chin down) and sips of water as you advance
- Stop and pull back for respiratory distress, inability to speak, heavy nosebleed, or resistance
- Confirm placement (X-ray), then tape to the nose and pin to the gown with slack
Decompression (suction)
- Removes air and fluid for bowel obstruction, paralytic ileus, or GI surgery; stays until bowel sounds or flatus return
- Single-lumen (Levin) tube: low intermittent suction to protect the stomach lining
- Double-lumen sump (Salem) tube: the blue air vent is never clamped, connected to suction, or used for irrigation; keep it above the stomach
- Irrigate with 20–30 mL of normal saline or water and count it as intake; frequent oral care; water-soluble (not petroleum) lubricant for the nares
- Heavy NG output loses fluid and electrolytes: watch for fluid volume deficit and metabolic alkalosis
Removal
- Verify the order; turn off suction; flush with 10 mL of saline or 30–50 mL of air
- Client takes a deep breath and holds it (closes the airway)
- Pinch the tube and withdraw it steadily; never force it; then mouth care
Gastric lavage (irrigating the stomach) uses a large-bore tube, mostly in the emergency department. It isn't routine for poisoning anymore. Never leave the client alone during it.
Tubes at a glance
| Tube | Goes where | Used for | Key points |
|---|---|---|---|
| NG (nasogastric), small-bore | Nose → stomach | Short-term feeding (under about 4 weeks) | Measure nose → earlobe → xiphoid, then add 10 cm; X-ray before the first feeding |
| Nasoduodenal / nasojejunal | Nose → past the stomach into the small intestine | Short-term feeding when the stomach shouldn't be used (slow stomach emptying, reflux, past aspiration pneumonia) | Longer measurement; lower aspiration risk |
| G-tube / PEG | Through the abdominal wall into the stomach | Long-term feeding | PEG is the most common placement; watch the site for infection |
| J-tube (jejunostomy) | Through the abdominal wall into the jejunum | Long-term feeding | Feeds past the stomach |
| Levin (single-lumen NG) | Nose → stomach | Decompression (removing air and fluid) | Low intermittent suction |
| Salem sump (double-lumen NG) | Nose → stomach | Decompression | Blue air vent: never clamp it; keep it above the stomach |
| Large-bore orogastric or NG | Mouth or nose → stomach | Lavage (washing out the stomach) | Emergency use; never leave the client alone |
Needs a pump: continuous tube feedings and IV potassium; an IV pump also helps prevent fluid overload. No pump needed: an intermittent (bolus) tube feeding can run by gravity or syringe.
Parenteral nutrition
Parenteral nutrition gives nutrients IV, for clients who can't meet their needs by mouth or tube.
- Through a CVAD or a peripheral vein, depending on how concentrated the solution is
- TPN (total parenteral nutrition): highly concentrated; provides all daily needs
- PPN (partial parenteral nutrition): provides part of daily needs
- Glucose abnormalities are common with TPN: monitor blood glucose
Parenteral nutrition should be short-term. Using the GI tract is preferred, because it keeps the gut working.
If the gut works, use it. Mouth first, then a tube (enteral), and IV (parenteral) only when the gut can't be used.
Parenteral nutrition holds dextrose, amino acids (protein), lipids, electrolytes, vitamins and minerals, mixed for each client. High blood glucose is the common problem: check glucose often; insulin can be added to the bag or given under the skin. Labs also track electrolytes and kidney and liver function. Never give other IV medications through the parenteral nutrition line. Lipid tubing is changed every 12 hours and with each new container.
Quick check
What's the gold standard for confirming feeding tube placement?
X-ray, before the first feeding or medication.
The gastric residual is 80 mL. Return it or discard it?
Return it (less than 100 mL).
Head of bed during a tube feeding, and for how long after?
30–45° during, and at least 30° for 1 hour after.
Which feeding method requires a pump?
Continuous feeding.
How much water before and after medications through a feeding tube?
30 mL before and 30 mL after.
Which lab do you watch most closely with TPN?
Blood glucose.